AI Scribes in Emergency Medicine: Tips from the ED


Emergency departments (EDs) combine high patient loads, time pressure, frequent interruptions and a heavy documentation burden. Dr Hassan Ahmad, a Provisional Fellow in Emergency Medicine and Certified Health Informatician, has used Lyrebird in this setting. He reports greater efficiency, more accurate and comprehensive clinical notes, the ability to see more patients and discharge them sooner, less cognitive load from delayed transcription, and greater enjoyment of his work. Achieving those gains depends on matching the capture method to the encounter and treating every output as a draft for clinical review.
What an AI scribe can do in the ED
An AI medical scribe captures a clinical conversation or clinician dictation and turns it into a structured draft note. The clinician then checks, edits and signs the note before it enters the patient record.
That boundary is especially important in emergency medicine. A scribe can organise the information it receives. It cannot see an examination finding, reconcile an electronic medication list, know which result changed the disposition, or document clinical reasoning that was never expressed. Those details still need deliberate input and verification against the source record.
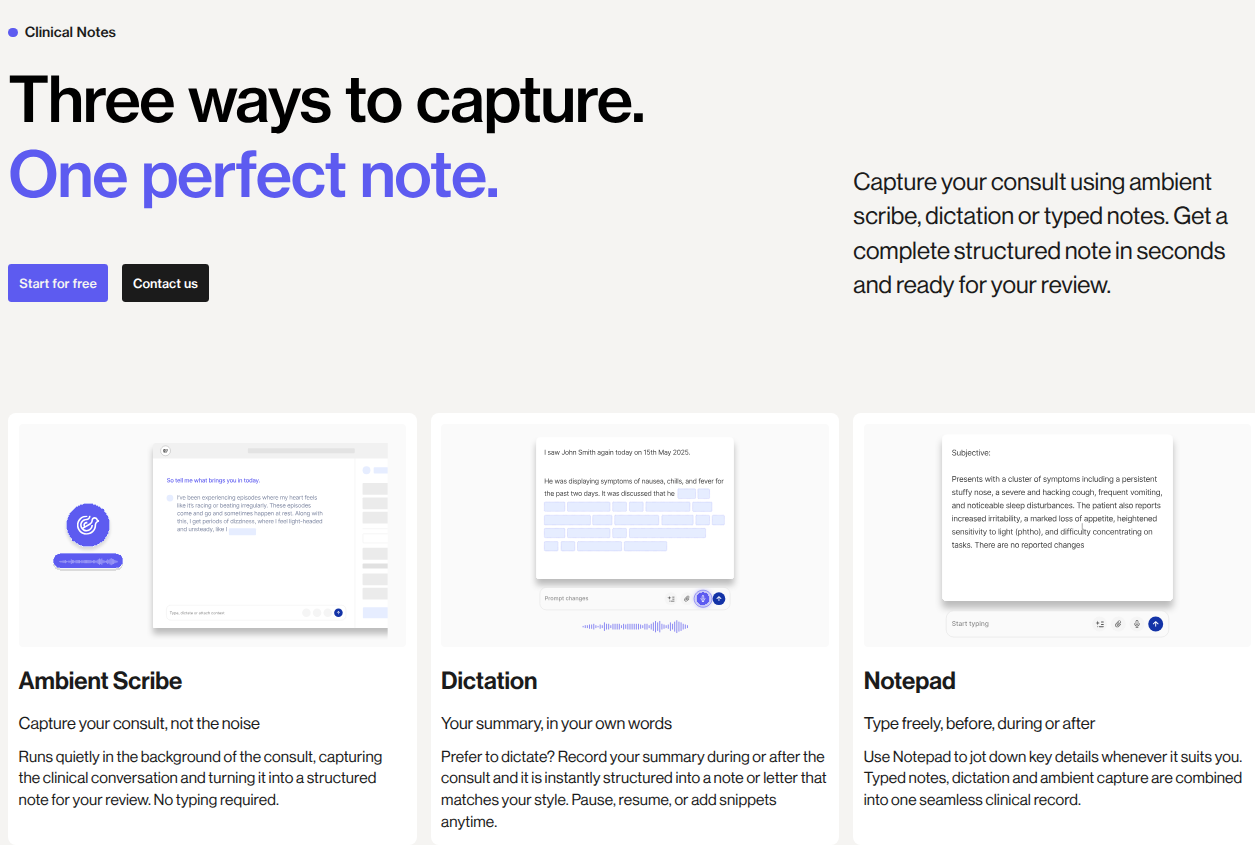
Ambient capture is one part of the workflow. Lyrebird's clinical notes also accept clinician dictation and typed Notepad details, which can feed the same draft. A clinician can capture a coherent history ambiently, dictate the examination and impression, then type a result or collateral detail that was never spoken at the bedside. Pause and resume also helps when the encounter unfolds over several conversations.
Custom templates can follow the ED's preferred structure, including presenting history, source of history, examination, investigations, clinical impression, ED course, procedures, disposition and safety-net advice. The clinical standard remains the same: capture, draft, reconcile and sign off.
For a health service rollout, Lyrebird supports controlled enterprise deployment, organisation-level sharing, onboarding and direct electronic medical record (EMR) integration for compatible systems. Australian patient data is processed and stored in Australia. Speech is converted to text in real time and the audio is then destroyed. Notes and transcripts are not used to train external AI models.
What current ED evidence shows
Dr Ahmad's reported experience is one clinician's account. The growing ED research base suggests that AI scribes can reduce documentation effort for some clinicians and encounters. It also shows selective uptake, continued editing and uneven performance across note sections.
| Study | Setting and design | Main finding | Important limitation |
|---|---|---|---|
| St Vincent's Hospital Melbourne, 2026 | Five-week single-arm observational study; 248 presentations | Modelled documentation saving was 7.1 hours for an average typist and 4.9 hours for a fast typist across 248 notes | Savings were calculated from typing, reading and editing assumptions, rather than measured end-to-end workflow time |
| Four-ED pilot survey, 2026 | 14 adult and paediatric emergency physicians | 71.4% reported better documentation efficiency and 64.3% less after-shift documentation | Only 42.9% trusted AI note accuracy; perceived usefulness was lower for physical examination and medical decision-making |
| AI versus human scribes, 2026 | Quality-improvement pilot; 710 adult and paediatric visits | Adult note-quality scores were similar | Compared with human-scribed notes, AI-assisted notes took more clinician time in the notes section and required a larger physician contribution; paediatric scores were lower |
| Ambient adoption study, 2026 | Retrospective study; 8,740 eligible adult ED encounters | Median on-shift documentation time was 2:45 with ambient AI and 3:50 with standard documentation | Only 11.2% of eligible encounters used ambient AI; use concentrated among a small group and in selected settings |
| Four-hospital comparison, 2026 | Retrospective study; 198,178 ED encounters | Adjusted median documentation time was 1.6 minutes shorter per note with ambient AI than with no scribe; human scribes were 3.3 minutes shorter | Work relative value units per shift hour did not differ between groups |
The useful conclusion is modest. An AI scribe can reduce documentation time compared with working without a scribe, but it does not make every note faster or prove an increase in ED productivity. Compared with a trained human scribe, it may require more physician editing. Results from one product, hospital or early-adopter group also do not establish how every scribe will perform in another ED.
Match the device to the clinical area
Fast track, acute and subacute bays, resus and waiting-room assessments all create different practical constraints. The capture device should suit the patient's location and the clinician's need to move.
- Mobile device or smartphone: A phone offers the most mobility, including at the bedside and in spaces where a computer on wheels will not fit. In a non-integrated setup, Dr Ahmad captures and saves the note in the Lyrebird app, opens it through the website at a workstation, reviews it and transfers the final text into the EMR. This adds several steps. A tap-on, tap-off virtual desktop can make the process easier because the browser session follows the clinician between workstations.
- Computer on wheels: This can be a useful compromise between mobility and EMR access. Availability is often the limiting factor, and the device may become an obstacle in a confined room or during a resuscitation.
- Fixed workstation: A fixed computer works well in a dedicated consultation room. It is less useful when the assessment moves between the bedside, corridor and another clinical area.
- Lapel or external microphone: A microphone attached to a workstation or computer on wheels may improve capture while preserving mobility. Any use needs to meet the hospital's device, infection-control and information-security requirements.
Personal and hospital-issued devices must follow the organisation's privacy, security and access policies. A convenient microphone does not make an unapproved application or personal account acceptable for clinical information.
Choose the capture method for the encounter
Ambient capture tends to suit a stable patient who can give a coherent history. A real-world study of 8,740 adult ED encounters found that use clustered in lower-acuity, conversational settings and encounters without an interpreter. Dr Ahmad similarly changes modes when the clinical circumstances change.
| ED situation | Sensible starting mode | Details to add deliberately |
|---|---|---|
| Stable patient with one clear presenting problem | Ambient capture | Examination, results, impression, disposition and safety-net advice |
| Stable patient with several issues | Ambient capture plus a dictated summary | Problem prioritisation, relevant negatives, reasoning and final plan |
| Interrupted encounter with ambulance, family or nursing collateral | Pause and resume, then dictate a consolidated summary | Information source, discrepancies, chronology and capacity limitations |
| Interpreter-mediated or overlapping conversation | Use only within the approved interpreter and consent workflow, then dictate key facts | Speaker attribution, exact meaning, uncertainty and translated instructions |
| Confused, non-verbal or critically unwell patient | Clinician dictation or a structured manual template | History source, examination, resuscitation events, timings and decisions |
| Procedure, reassessment or handover | Separate structured template or focused dictation | Indication, consent, technique, medicines, complications, response and outstanding actions |
Switching to dictation is good practice when ambient capture no longer fits. It prevents a noisy or fragmented recording from becoming the only source for a complex note.
Obtain and record consent before capture
Before ambient capture begins, the patient needs a clear explanation of what the tool does, what information it handles and how it supports the note. The patient must be able to raise concerns or decline without affecting their care. Any consent required for the specific patient, capture method, applicable state or territory law and hospital policy should be obtained and recorded before capture.
AHPRA's AI guidance says an AI scribe using personal data will generally require informed consent, with the patient's response ideally noted in the health record. It also keeps accountability with the practitioner, including responsibility for checking the accuracy and relevance of the generated record.
High-acuity care needs a planned alternative. A patient who cannot consent during a major trauma, cardiac arrest or another critical presentation should not be recorded simply because the situation is urgent. Clinicians need to follow the hospital's approved pathway or document through clinician dictation after the encounter. Family involvement, substitute decision-making and emergency exceptions depend on the patient's circumstances and the applicable legal and organisational framework.
The product's intended purpose also affects its regulatory position. The TGA's digital scribe guidance says software intended only to transcribe and translate a clinical conversation into a written record, without analysis or interpretation, is not a medical device. A product that generates a diagnosis, differential diagnosis or treatment recommendation that the clinician did not explicitly state is a medical device and must be included in the Australian Register of Therapeutic Goods before supply in Australia.
Capture information across interruptions
An ED consult rarely happens as one uninterrupted conversation. A clinician may start with the patient, pause to examine them, obtain collateral history from family, speak with ambulance or nursing staff, then return after pathology or imaging. Pause and resume lets those relevant parts contribute to the same draft without recording unrelated clinical work in between.
The source of information also needs to be explicit. The final note should distinguish what came from the patient, a family member, ambulance staff, an interpreter or the previous record. If accounts conflict, the draft should preserve that uncertainty rather than merge them into one confident narrative.
Verbalise discrete clinical details
An ambient scribe only receives what is said within its capture. In Dr Ahmad's workflow, medication names, doses and frequencies are read aloud when he reviews a Webster pack or medicine chart. Repeating important parts of the history back to the patient can confirm understanding and give the scribe a clearer account to structure.
State examination findings
Physical findings are often visual or tactile. Dr Ahmad verbalises relevant findings after the examination, such as bilateral air entry or focal abdominal tenderness, then checks that the draft reflects what he observed. This technique takes practice and should never direct the examination itself.
Articulate the impression and plan
Explaining the working impression and management plan to the patient can support their understanding and give the scribe material for the draft. The clinician still needs to review the final clinical reasoning and add results, risk assessment, important differentials actually considered, response to treatment and the rationale for disposition when these were not captured in the conversation.
Review and augment every draft
Dr Ahmad regards the first output as a preliminary draft. The 2026 Melbourne study found that clinicians made 1,143 modifications across 248 AI-assisted notes. The history of presenting illness and management plan were the most frequently revised sections. Review effort is therefore part of the workflow, rather than an optional final glance.
Every review should include:
- confirming the correct patient, encounter and participants
- checking the history, chronology, relevant negatives and information sources
- validating allergies, medicines, doses, past history and comorbidities
- confirming that examination findings were observed and stated accurately
- reconciling observations, pathology and imaging with source records
- adding clinical reasoning, consultations, procedures, reassessments and response
- checking disposition, follow-up, return advice and outstanding actions
- removing unsupported, contradictory, duplicated or irrelevant text
The time measure that matters is end to end: generation, review, correction and write-back. A draft produced in seconds has little value if it takes longer to repair than the clinician's usual note.
Use the note for clearer discharge communication
Once the clinician has reviewed the clinical note, Lyrebird can use the same patient context to draft a discharge letter or a separate patient-facing summary. Dr Ahmad finds the distinction useful because the technical record and the information a patient needs at home serve different purposes.
The first discharge draft may be too long. Dr Ahmad refines it to the diagnosis or working impression, treatment given, medicine changes, follow-up and specific return advice. A patient-facing version should use plain language without weakening the safety message.
Automatically translated patient information needs its own approved workflow and suitable verification. It does not replace a credentialed interpreter and should not be used where the health service has not assessed the clinical and medico-legal risks.
Keep clinical devices clean
Phones, external microphones and computers on wheels introduce additional high-touch surfaces. Dr Ahmad disinfects the equipment between patients according to local infection-prevention policy and keeps it out of sterile or restricted areas unless it is approved for that use.
Measure the whole workflow before scaling
A department-wide rollout should start as a controlled pilot. It can begin with consenting, stable patients in a conversational clinical area, then expand after the team understands where the tool helps and where it creates work.
Useful measures include:
- eligible encounters in which clinicians actually use the scribe
- end-to-end documentation time and after-shift documentation
- notes finalised before disposition or handover
- corrections by note section, including omissions, unsupported statements and contradictions
- patient decline rate
- privacy, security and wrong-patient incidents
- clinician experience by role, seniority, shift and clinical area
The ED evidence shows why access alone is a poor success measure. Uptake may concentrate among trainees, early adopters and lower-acuity zones. A sound pilot tests the actual mix of clinicians and encounters, preserves an easy alternative when capture is unsuitable, and keeps clinical judgement at the centre of sign-off.
An AI scribe earns its place in an ED workflow when it produces a useful draft, keeps documentation closer to the encounter and gives the clinician more attention for the patient. It remains an assistant. The final record and the decisions behind it remain the clinician's responsibility.
Planning an emergency department pilot with Australian data handling, flexible capture and clinical governance in scope?